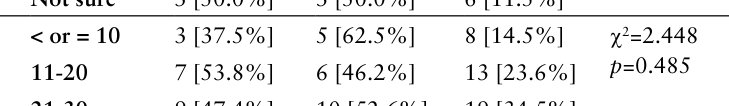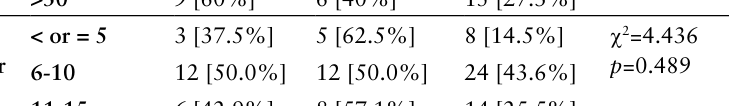Veronica Bessone (2026). Work Related Musculoskeletal Injury Rate and Ergonomics in Endourology: A Global Survey. In: Healthcare and Medical Devices. AHFE Open Access, vol. 211, pp. 212–221. https://doi.org/10.54941/ahfe1007484
Work-related musculoskeletal injuries (MSI) are frequent among urologists but often underrecognized, affecting both personal wellbeing and healthcare system efficiency. This study aimed to investigate the prevalence of work-related MSI and the correlation with anthropometric and work characteristics in endourology. Fifty-five endoscopists and nurses participated in a global online survey containing questions about anthropometrics, demographics, work and procedure characteristics. Work-related MSI were reported by 49% of respondents. No significant correlation was found between demographic, anthropometric or procedure characteristics and the occurrence of injuries (p>0.05). The most frequent affected areas were lower and upper back, wrist, and thumb. Prolonged procedural posture and repetitive movements were identified as the main contributing factors. Urologists performing more flexible than rigid or semi-rigid endoscopy reported a higher rate of upper back pain, while those sitting during the procedure reported a lower incidence of upper back MSI (p<0.05). 9% of participants had received ergonomic training. Limitations included the small number of nurses (n=2) and potential response bias. Our findings align with earlier studies, confirming a high work-related MSI prevalence among the urologists. This highlights the importance of implementing preventing measures before, during and after the procedures. Given the professional and economic consequences of work-related MSI, promoting ergonomic awareness is essential. Performing the procedure while sitting, use of two-piece lead aprons, pre-procedural warmups, and using light weight endoscope could improve urologist’s ergonomics and should be targeted in ergonomic training programs.
Urology comprehends different type of specialties as endoscopy (rigid and flexible), robotics and laparoscopy. This diversity of techniques and environments presents significant ergonomic challenges in daily clinical practice. Consequently, musculoskeletal injuries (MSIs) are frequent among urologists with a rate reaching up to 86% (Tjiam et al., 2014), with female specialists more affected (Razavi et al., 2025). MSIs are affecting not only the physical health of the professionals, but also their mental health, reflected by the high level of burnout among urologists, the highest among healthcare professionals (Razavi and De, 2023).
The evolution from rigid to flexible endoscopes, brought not only clinical, but also ergonomic advantages for the users, who do not need to Received January 29, 2026; Revised April 11, 2026; Accepted April 25, 2026; Available online July 20, 2026
Work Related Musculoskeletal Injury Rate and Ergonomics in Endourology: A Global 213 bend or stretch as much during the procedures as in the past. Endourology requires a physical interaction between the clinician and the device to insert, guide and manoeuvre the tip of the endoscope. Despite technological advancements, endoscope handle design has remained largely unchanged for decades (Talyshinskii et al., 2024). More recently, the introduction of single use endoscope allowed a reduction of the weight of the endoscope with consequent better ergonomics by lowering required muscle activation (Ludwig et al., 2017; Wright et al., 2022; Kim et al., 2024).
Ergonomics within the operating room has gained significant attention (Cohen et al., 2024), driven by the need to minimize workplace injuries and preserve career longevity amidst physician shortages (Kim et al., 2024), and accommodate the increasing number of female specialists (Nam et al., 2021). The rising prevalence of kidney stones (Chen et al., 2018; Bilal et al., 2019), coupled with a shortage of urologists, suggests that the frequency of ureteroscopy procedures per surgeon is likely to increase. This underscores the importance of preventive ergonomic strategies to promote a safe and sustainable working environment.
Although awareness of MSI in endourology is increasing, evidence on how anthropometric characteristics, ergonomic habits, and procedural behaviors relate to injury risk remains limited. To our knowledge, no study has yet explored the correlation between anthropometric characteristics, ergonomic practices, and the occurrence of MSI in urology. The aim of this study is to investigate these correlations and to assess the status of ergonomic training and preventive measures among urologists.
MATERIAL AND METHODS A world-wide online survey was conducted from March to September 2025 involving clinically active doctors and nurses working in urology. The survey was conducted according to the Declaration of Helsinki and the protocol approved by the ethical committee of Ambu (reference: ANI-0037/2025). The responders consented to participate in the study by submitting the anonymous, not compensated and voluntary survey. The potential participants were identified during international urology conferences and through newsletters. The questionnaire comprised 45 questions including anthropometrics, demographics, MSI experience and treatment, work-place characteristics and preventive measures such as ergonomic training. To allow comparisons with other fields of endoscopy and enhance content validity, the questions were based partially on a previously developed questionnaire by the author directed at gastrointestinal (GI) endoscopy (Bessone and Adamsen, 2022). The survey design allowed respondents to skip not applicable questions, which led to varying denominators across analyses; these are reported accordingly in the tables.
Descriptive statistics were used to analyse the data. A chi-squared test was performed to assess whether anthropometrical and demographic data, working setup or ergonomics characteristics were associated with MSI. The calculations were performed using IBM SPSS Statistics (IBM Corporation, Armonk, NY, USA). Statistical significance was set at p<0.05.
RESULTS
Fifty-six healthcare respondents participated in the survey; one subject was excluded being a student. Fifty-three were doctors and two were nurses, 93% were older than 35 years and 64% men (Table 1). Four endoscopists worked in the USA, 50 in Europe (Italy, Spain, Denmark, Netherlands, United Kingdom, Germany, Sweden, France) and one in Algeria.
Table 1: Responders’ anthropometric and descriptive data vs. development of work- related injuries (n [%]). The percentage is compared to the number of people in the relative group.
Work Related Musculoskeletal Injury Rate and Ergonomics in Endourology: A Global 215 Most of the responders (89%) had at least five years of experience and perform both cystoscopy and ureteroscopy (Table 2), with more than 10 hours/week of active use of the endoscope for 36%.
Table 2: Procedure characteristics and development of work-related injuries in endourology (n [%]). The percentage is relative to the number of people in the relative group.
>25 1 [25.0%] 3 [75.0%] 4 [7.3%] 1n=53, two subjects did not have the question. 2n=48, five subjects stated not to perform ureteroscopy and two did not have the question. 3n=49, six subjects did not answer the question. 4n=52, three subjects did not answer the question.
Ergonomic and work position characteristics are reported in Table 3. Only one subject stated to warmup (stretching, mobility exercises, etc.) before starting a procedure. Of the responders, 76% adjusted the monitor position, 91% the patient bed’s height, 82% the pedals’ position and 2% use a floor mat. Additionally, physicians wearing progressive/bifocal lenses were more inclined to adapt the position of the monitor and the patient’s bed to their height as well as the foot pedal placement (p<0.05). Endoscopists performing longer therapeutic ureteroscopy procedures were more commonly adjusting the height of the patient’s bed (p<0.05). Regarding the working position during the procedure, 29% reported to sit, while 31% reported that it
Work Related Musculoskeletal Injury Rate and Ergonomics in Endourology: A Global 217 depends on the procedure. 71% reported to use a single piece led apron, while 18% a two-piece. Ergonomic training had been completed by 9% of the professionals, with a significant gender difference (p<0.05). 53% would be interested in participating in an ergonomic training, with the interest significantly higher among those who experienced MSI (p=0.013). 9% did not perform any physical activity during the week. Among the physical activities, running and walking (n=23, both) were the most common, followed by cycling (n=18) and gym (n=16). 33% stated doing a leisure activity that involves the use of the fingers, i.e. videogames, playing a musical instrument.
Table 3: Responders’ ergonomic data and work-related injuries (n [%]). Statistical differences were calculated within the groups and significance is highlighted in bold (p < 0.05). The percentage is relative to the number of people in the relative group.
Table available in the original PDF paper.
Equation reproduced from the original PDF.
Warm up Yes 0 [0.0%] 1 [100.0%] 1 [1.8%] χ2=0.982 p=0.322 No 27 [50.0%] 27 [50.0%] 54 [98.2%] Adapt position of the monitor Yes 20 [47.6%] 22 [52.4%] 42 [76.4%] χ2=0.154 p=0.695 No 7 [53.8%] 6 [46.2%] 13 [23.6%]
Adapt position of patient’s bed
Yes 25 [50.0%] 25 [50.0%] 50 [90.9%] χ2=0.182 p=0.670 No 2 [40.0%] 3 [60.0%] 5 [9.1%] Use of floor mat Yes 1 [100.0%] 0 [0.0%] 1 [1.8%] χ2=1.020 p=0.312 No 24 [49.0%] 25 [51.0%] 49 [89.1%]
N/A 2 [40.0%] 3 [60.0%] 5 [9.1%] Adapt position of foot pedals Yes 24 [53.3%] 21 [46.7%] 45 [81.8%] χ2=0.681 p=0.409 No 3 [37.5%] 5 [62.5%] 8 [14.5%]
Depends 2 [100.0%] 0 [0.0%] 2 [3.6%] N/A 1 [25.0%] 3 [75.0%] 4 [7.3%] Yes 6 [37.5%] 10 [62.5%] 16 [29.1%] χ2=1.512 p=0.470 No 11 [50.0%] 11 [50.0%] 22 [40.0%] Sit while performing the procedure
Depends 10 [58.8%] 7 [41.2%] 17 [30.9%] Hand used to hold the endoscope Left 3 [50.0%] 3 [50.0%] 6 [10.9%] χ2=0.004 p=0.998 Right 22 [48.9%] 23 [51.1%] 45 [81.8%]
Depends 2 [50.0%] 2 [50.0%] 4 [7.3%] Had ergonomic training Yes 4 [80.0%] 1 [20.0%] 5 [9.9%] χ2=2.103 p=0.147 No 27 [54.0%] 23 [46.0%] 50 [90.1%]
Equation reproduced from the original PDF.
Interested in ergonomic training Maybe 7 [41.2%] 10 [58.8%] 17 [30.9%]
218 Bessone 49% of the responders experienced at least one work-related MSI, located mainly in the lower back and thumb (n=10, both), wrist (n=9), neck (n=8) and shoulder (n=7). When in a limb, MSIs were in 16 cases on the right side and in four on the left. The MSI limited the physicians to go to work for two subjects. Muscle/tendon strain was the most common MSI (n=9), followed by tendinitis (n=7) and tension neck and mechanical back syndromes (n=5, both). Analgesics (n=9) and anti-inflammatory medication (n=8) were the most frequently used intervention, followed by rest (n=6) and exercise (n=5). According to the injured responders, the cause leading to their MSIs was the position maintained during the procedure (n=14), and the repetitive movements (n=9). The weight (n=8) and size of the handle (n=6) were the most cited MSI causes related to the endoscope. Using lighter ureteroscopes and cystoscopes were the most requested changes towards the manufacturers (57% and 36%, respectively), with 60% of female and 51% of male physicians wanting lighter ureteroscopes.
Anthropometric or descriptive characteristics demonstrated not to be risk factors of MSIs (p>0.05). Urologists performing more flexible than rigid/ semi-rigid endoscopy had a higher risk of upper back pain, but a lower risk of developing wrist MSIs (p<0.05). No correlations were found between the duration of therapeutic and diagnostic ureteroscopies and the onset of MSIs, but to shorter diagnostic and therapeutic cystoscopies correlated a lower risk of developing upper back MSIs (p<0.05). Urologists sitting while conducting a procedure reported a lower incidence of upper back MSI (p=0.006). Having smaller hands (glove size ≤ 6.5) did not relate to having experienced a MSI of the thumb or fingers.
DISCUSSION
Recently, ergonomics has gained significant attention in urology, driven by the need of reducing workplace injuries. This is essential not only to preserve the career longevity of the physicians, but also to keep their health to cover the increasing number of procedures (Chen et al., 2018; Bilal et al., 2019). In this study, 49% of the surveyed professionals had experienced at least one work-related MSI, which is in line with a previous publication reporting occurrences up to 86% (Tjiam et al., 2014).
No anthropometric or demographic factors were significantly associated with MSI occurrence. This contrasts with previous reports, such as Tjiam et al. (2014), who found higher MSI rates among younger physicians, and Razavi et al. (2025), reporting higher rates among female urologists. None of the procedure characteristics were linked to a higher risk of developing MSI. This aspect differs from GI endoscopy in which a higher procedure volume was linked to a higher MSI rate (Bessone and Adamsen, 2022). A possible explanation is that endoscopy constitutes only one part of the urologist’s clinical workload, and other tasks may contribute more substantially to physical strain. In fact, the weekly procedural volume and hours of active endoscope use reported in this study were considerably lower than those reported in GI endoscopy (Bessone and Adamsen, 2022).
The back was the primary locations of MSI, in line with past studies (Elkoushy and Andonian, 2011; Lloyd et al., 2019). When located in a
Work Related Musculoskeletal Injury Rate and Ergonomics in Endourology: A Global 219 limb, MSI have been reported to be distributed mainly in the hand holding the endoscope. Most of the physicians reported not taking any remedy, as seen previously (Omar et al., 2020), and none stated to have had a surgery due to MSI. However, 7% of injured respondents had taken time off work, highlighting the broader impact of MSI on personal and professional life. Absenteeism among urologists can impose substantial costs on healthcare systems, with two weeks of missed work estimated at approximately $100,000 (Zampini, 2025). This underscores the economic impact of ergonomic interventions, which may be justified through cost-benefit analyses of training programs and equipment redesign.
As other fields of endoscopy, also endourology can be considered as a high-intensive endurance activity, with long procedure time applying forces and torques, and wearing heavy lead aprons. Pre-procedural warmups have shown to be beneficial in GI endoscopy (Siau and Anderson, 2019) but remain uncommon in urology—only one respondent in this survey reported performing them. Given the physical load associated with endourology, the integration of structured warmups, recovery protocols, and ergonomic routines could meaningfully reduce fatigue and MSI risk. Maintaining an active lifestyle is also recommended to prevent work- related injuries, as supported by evidence from dentists (Sharma and Golchha, 2011), and surgeons (Kitzmann et al., 2012), and should be extended to urologists.
Respondents frequently identified nonergonomic working positions, repetitive movements, and endoscope design features (e.g., weight and handle size) as contributors to MSI. This reinforces the importance of optimizing equipment positioning within the endoscopy suite. Proper adjustment of monitor height and angle, patient bed position, and footpedal alignment is known to reduce neck, shoulder, spine, and arm strain (Gabrielson et al., 2021). Despite these recommendations, the present study found no correlation between equipment adjustments and MSI occurrence—likely due to a ceiling effect, as most participants already reported practicing these adjustments. Corrective lenses pose an additional ergonomic consideration. Previous research showed an association between wearing bifocals/progressive lenses and neck discomfort in GI endoscopy due to limitations in monitor positioning (Shergill et al., 2009). In this study, endourologists with progressive lenses were more likely to adjust monitor and bed height, suggesting increased compensatory behavior. Sitting during procedures emerged as a potentially protective factor; respondents who sat reported lower rates of upperback MSI. This could be explained by reduced spinal load from lead aprons and improved postural stability when operating foot pedals in a seated position. Regarding lead protection, twopiece aprons are generally recommended, as they distribute weight more evenly between shoulders and hips (Gabrielson et al., 2021).
As in a previous study of the author (Bessone and Adamsen, 2022), “Ergonomic Time-out” is recommended to prepare the endoscopic room, to ensure the correct equipment positioning and to perform a warmup. All the above-mentioned best practices can be taught during specific ergonomic training. Unfortunately, only a small portion of the urologists have received
220 Bessone one (11%), despite its potential benefits in reducing MSI has been proven in other medical specialties (Berquer et al., 2002; Edelman et al., 2017). The importance of ergonomic training is nonetheless recognized by endoscopists who had experienced MSI, and they reported to be willing to participate in such training. This mismatch highlights a critical opportunity for structured educational initiatives.
A limitation of the study is the low number of nurses participating. Besides being heavily physically involved during the procedure, in several countries nurses are also performing routine cystoscopies such as stent removal. Potential response bias should also be considered, since physicians with past or current experience of MSI could have been more likely to respond to the survey. Moreover, future investigations should involve a higher number of participants with an even wider geographical distribution. Looking ahead, the increasing representation of women in urology (Nam et al., 2021; Marlicz et al., 2021), and ongoing technological advancements in endoscope design (Talyshinskii et al., 2024), may influence ergonomic needs and solutions. Future studies should explore whether newer scopes with improved ergonomics reduce MSI risk.
CONCLUSION
MSIs are frequent among healthcare professionals within urology, yet awareness of work-related injuries remains limited. This gap perpetuates the persistent taboo that physicians cannot be sick—an assumption that not only undermines their wellbeing but also compromises the sustainability of healthcare delivery. The impact of MSI on both private and professional life of the physicians, as well as on the healthcare and social system cannot be denied. This study shows that urologists are no exception regarding high incidence of MSI. The low adoption of ergonomic training underscores the need for structured interventions, including the implementation of an “ergonomic time-out”.
ACKNOWLEDGMENT
The author is grateful to the physicians participating in the survey.
REFERENCES
Berquer R, Smith WD, Davis S. (2002). An ergonomic study of the optimum operating table height for laparoscopic surgery. Surg Endosc, 16(3), 416–21. Bessone V, Adamsen S. (2022). Gastrointestinal endoscopy and work-related injuries:
an international survey. Endosc Int Open, 13, 10(5), E562–E569. Bilal K, Tomer N, Kaplan-Marans E, Finkelstein M., Palese M. (2019). MP08-12 Utilization trends and 90-day treatment-free rates for ESWL, URS, and PCNL cases in the inpatient and outpatient setting between 2004–2014. J Urol, E102– E103. Chen Z, Prosperi M, Bird VY. (2018). Prevalence of kidney stones in the USA: the
national Health and nutrition evaluation survey. J Clin Urol,12(4), 296–302.
Work Related Musculoskeletal Injury Rate and Ergonomics in Endourology: A Global 221 Cohen TN, Kanji FF, Anger JT. (2024). The Application of Human Factors
Approaches to Improve Safety, Efficiency and Well-being in Urology: A Systematic Scoping Review. Urology, 194, 295–309. Edelman K et al. (2017). Endoscopy-related musculoskeletal injury in AGA gastroenterologists is common while training in ergonomics is rare. Gastroenterol, 152(5), S217. Elkoushy MA, Andonian S. (2011). Prevalence of orthopedic complaints among
endourologists and their compliance with radiation safety measures. J Endourol, 25(10), 1609–13. Gabrielson AT, et al. (2021). Surgical ergonomics for urologists: a practical guide.
Nat Rev Urol, 18(3), 160–169. Kim E et al. (2024). Gender differences in ergonomics during simulated ureteroscopy.
Am J Surg, 235, 115691. Kitzmann AS, Fethke NB, Baratz KH, Zimmerman MB, Hackbarth DJ, Gehrs KM.
(2012). A survey study of musculoskeletal disorders among eye care physicians compared with family medicine physicians. Ophthalmology, 119(2), 213–20. Lloyd GL, Chung ASJ, Steinberg S, Sawyer M, Williams DH, Overbey D. (2019).
Is Your Career Hurting You? The Ergonomic Consequences of Surgery in 701 Urologists Worldwide. J Endourol, 12, 1037–1042. Ludwig WW, Lee G, Ziemba JB, Ko JS, Matlaga BR. (2017). Evaluating the Ergonomics of Flexible Ureteroscopy. J Endourol, 31(10), 1062–1066. Marlicz W, Koulaouzidis A, Koulaouzidis G. (2021). Future endoscopy-related
injuries will be of different types and gender-equal. Am J Gastroenterol 2021;116:1960–1961. Nam CS, Daignault-Newton S, Herrel LA, Kraft KH. (2021). The Future is Female: Urology Workforce Projection From 2020 to 2060. Urology, 150, 30–34. Omar M, Sultan MF, El Sherif E, Abdallah MM, Monga M. (2020). Ergonomics
and musculoskeletal symptoms in surgeons performing endoscopic procedures for benign prostatic hyperplasia. Ther Adv Urol, 20, 12:1756287220904806. Razavi S, De EJB. (2023). Ergonomics in Urology: Silent Contributor to Burnout Among Women in Urology? Urology, 173, 222–225. Razavi S, et al. (2025). Urologist’s Fatigue and Discomfort in Different Body Regions
After Performing Flexible Ureteroscopy. Urology, 200, 238–244. Sharma P, Golchha V. (2011). Awareness among Indian dentist regarding the role of physical activity in prevention of work related musculoskeletal disorders. Indian J Dent Res, 22, 381–384. Shergill AK, McQuaid KR, Rempel D. (2009). Ergonomics and GI endoscopy.
Gastrointest Endosc, 70, 145–153. Siau K, Anderson JT. (2019). Ergonomics in endoscopy: Should the endoscopist be considered and trained like an athlete? Endosc Int Open, 7, E813–E815. Talyshinskii A et al. (2024). Being all-seeing gymnast within kidney cavity: analysis
of the optical and flexibility characteristics trends of 61 flexible ureteroscopes over four decades. Urolithiasis, 17, 52(1):92. Tjiam IM et al. (2014). Ergonomics in endourology and laparoscopy: an overview of musculoskeletal problems in urology. J Endourol, 28(5), 605–11. Wright HC et al. (2022). Ergonomics in the OR: An Electromyographic Evaluation
of Common Muscle Groups Used During Simulated Flexible Ureteroscopy - a Pilot Study. Urology,170, 66–72. Zampini A. Ergonomics Matter. OR injuries and prevention. American Urology Association (AUA) Conference 2025. 26th-29th April 2025. Las Vegas. USA
LISTED IN THE AHFE DIGITAL BOOKSTORE CATALOGUE
Explore the complete digital volume
Healthcare and Medical Devices
Read this individual research paper free through the original publisher, or explore the full digital proceedings book.
ISBN 978-1-964867-87-8
Explore this ISBN in the AHFE Bookstore ↗Listed in the July 2026 bookstore catalogue; search by ISBN to confirm current availability · Digital book purchase optional