Yoshitaka Maeda (2024). Clarification of drug-checking strategies for expert pharmacists based on gaze analysis. In: Healthcare and Medical Devices. AHFE Open Access, vol. 130, pp. 109–119. https://doi.org/10.54941/ahfe1004844
In Japan, a pharmacist who receives a physician’s prescription for a drug (1) checks the medical and pharmacological validity of the prescription; (2) prepares the drug; and (3) confirms that the drug has been prepared as prescribed, and that there are no quality issues. The aforementioned checkpoints (1) and (3) are particularly important for ensuring patient safety. Meanwhile, knowledge of checking is tacit and not shared among pharmacists. Therefore, a pharmacist’s gaze was analyzed to identify checking strategies based on expert gaze patterns. Gazing points in prescriptions during expert checks were measured in a clinical setting. Four participants had 20–30 years of experience as pharmacists. Consequently, four check strategies were identified. However, the check strategy differed, depending on the participant. This indicates that each pharmacist in charge of checking prescriptions has a different strategy, and that there are errors that are difficult to detect. In the future, it is necessary to verify the validity of these strategies in terms of safety, and to develop methods to educate novices in a well-balanced manner in each of these strategies.
Pharmacists play an important role in providing effective and safe medical care (Arakawa, 2022). Countermeasures against unsafe or unjustified drug treatments are a global healthcare safety issue. The World Health Organiza- tion has set a goal of 50% reduction in drug-related avoidable harm globally by 2022 (World Health Organization, 2017; Sheikh et al. 2019). There- fore, various measures, including computerized drug ordering, barcode drug matching, automated dispensing devices, and contraindicated drug-checking systems, have been implemented to improve drug safety in hospitals (Hirano et al. 2017; Kawamoto et al. 2009; Kunitsu et al. 2020; Shah et al. 2016). However, medication errors continue to occur and cause serious harm to patients (Council of Europe, 2007; Wahr et al. 2014). A total of 1,539 med- ical incident reports were submitted to the Japan Medical Safety Research Organization in five years to September 2020, of which 273 (17.7%) were drug-related fatalities (Japan Medical Safety Research Organization, 2022).
Additionally, >2,000 drug-related incidents are reported annually at the Jichi Medical University Hospital.
In Japan, a pharmacist who receives a physician’s prescription for a drug (1) checks the medical and pharmacological validity of the prescription; (2) prepares the drug; and (3) confirms that the drug has been prepared as pre- scribed, and that there are no quality issues. The aforementioned checkpoints (1) and (3) are particularly important for ensuring patient safety. Many inci- dents have been attributed to omissions in the detection of errors due to inadequate prescriptions and drug checks.
Furthermore, efficient checking strategies are important. The workload of pharmacists in many hospitals is high. For example, at the Jichi Medical Uni- versity Hospital, approximately 20 pharmacists dispense >1,000 inpatient medications daily. Medical care sophistication has increased the complexity of pharmaceutical operations. There are many different prescription drugs, and the time required to check each case is long. Novice pharmacists often check drugs in busy situations. Novices also have expertise in pharmacies; however, their knowledge and skills necessary for safe and efficient checking are lacking and error-prone. Therefore, quality education on safety-related operations is essential. However, in many hospitals, pre-graduate and novice education are insufficient (Vosper and Hignett, 2018). For example, many hospitals use manuals that summarize standard procedures (e.g., checking drug specifications) for education. However, education on specific methods (how to check) is left to each instructor, resulting in variation in education quality. This is partly because the knowledge of safe and efficient checking is tacit.
Therefore, the drug-checking strategies of expert pharmacists must be identified and shared effectively and efficiently among pharmacists. This is expected to allow novices to check and improve their dispensing accuracy and operational efficiency. However, extracting tacit knowledge through simple interviews is difficult. Some industries use expert gaze data to clarify tacit knowledge (Morita et al. 2018; Udagawa 2020; Yamashita et al. 2019).
Hence, in this study, gaze analysis of pharmacists was performed to identify check strategies based on expert gaze patterns.
METHODS
Gazing points during expert checks were measured in a clinical setting (see Figure 1). Four participants had 20–30 years of experience as pharmacists. Each participant wore an eye-mark recorder (Tobii Pro Glasses 2), and gaze data were recorded during a 5-min check. Sampling rate was set at 100Hz, and the four participants checked 24 prescriptions and drugs within 5 min. Eye detection rate from the start to the end of the task was >60% for all the four participants. Tobii Pro Studio (Tobii Technology, Inc., Stockholm, Sweden) was used to analyze the gazing-point videos. The gaze points for each participant were extracted by slowing down the gaze video to 1/16th of the original speed. Based on previous studies (Fukuda et al. 1996) on the definition of gaze point, we confirmed the gaze point by replaying the videos frame by frame, and defined the gaze point as a pause of >0.133 s. Gazing
Clarification of Drug-Checking Strategies for Expert Pharmacists Based on Gaze Analysis 111
duration, number of gazes at the area of interest (AOIs), and order of gazes between AOIs were recorded.
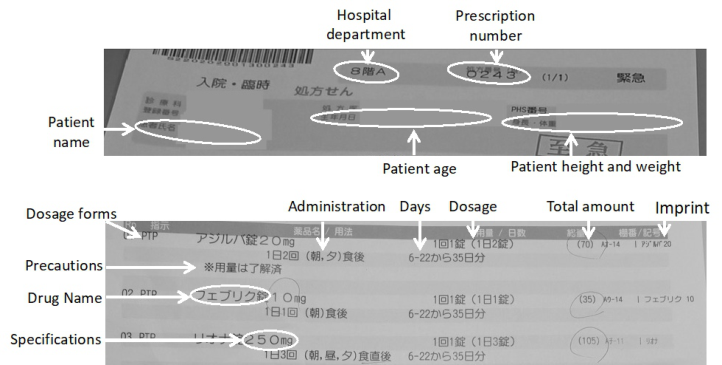
First, gazing pattern at prescriptions, which is the most important source of information during drug checks, was identified. Twenty-four prescription checks were classified using factor analysis based on the duration of gazing at 15 prescription AOIs (see Figure 2). Based on a scree plot, the number of factors was set to four, and principal axis factoring and promax rotation were used.
Next, a scan-path diagram was created to visualize 24 check gazings clas- sified using factor analysis. This is a visualization of the percentage of gaze duration for each AOI relative to the total gaze duration (percentage of gaze duration), as well as the direction and number of movements between AOIs (Aoki et al. 2019; Aoki and Suzuki, 2010; Itoh et al. 1998). First, the per- centage of the gaze duration for each AOI was expressed in terms of the area
112 Maeda
of the circle. Next, for each AOI, the direction of gaze movement was repre- sented by arrows. The thickness of the arrows corresponds to the number of movements. The AOIs of the prescription are shown in Figure 2; the AOIs of the medicine bag are patient name, drug name, prescription number, admin- istration, dosage, days, date dispensed, pharmacist name, and precautions. The AOIs of the drug are patient name, drug name, prescription number, quantity of drug, packaging, imprint, and expiry date.
This study was conducted in accordance with the Declaration of Helsinki, and was approved by the Ethics Review Committee of Jichi Medical Univer- sity (23-005). We explained that consent to participate in the study could be withdrawn at any time, that the results of this study would be published after processing, and that the participants’ personal information would not be revealed in the publication.
RESULTS
Table 1 summarizes the gaze data of the four experts. The number of AOIs and mean number of eye movements in participants 2 and 4 tended to be low, and the mean duration per fixation tended to be long. In other words, participants 2 and 4 focused on referring to less information when checking. Conversely, participants 1 and 3 had more information-based checks.
Table 2 shows the results of the factor analysis based on the gaze duration at the prescription AOIs. Factor 1 consisted of three AOIs regarding adminis- tration and precautions from a physician regarding dosage. Therefore, it was referred to as detection of administration errors.
Table 1. Summary of gazing data for each participant.
Factor 2 consisted of AOIs for understanding a patient’s disease, such as information on the background of dispensing, patient’s age, and hospital department. This was called the detection of inappropriate prescriptions for symptoms.
Clarification of Drug-Checking Strategies for Expert Pharmacists Based on Gaze Analysis 113
Table 2. Factor analysis pattern matrix based on gazing duration of AOIs on prescription (principal axis factoring, promax rotation).
Table available in the original PDF paper.
AOIs Factor 1 Factor 2 Factor 3 Factor 4
29.80 44.17 53.49 60.54
Factor 1: Detection of administration errors Administration 0.986 0.052 −0.099 −0.042 Precautions 0.942 −0.137 0.2 −0.206 Dosage forms 0.728 0.092 −0.098 0.2 Factor 2: Detection of inappropriate prescription for symptoms Pharmacist name 0.029 1.034 -0.267 0.048 Patient age −0.012 0.763 0.155 0.01 Hospital department −0.027 0.496 0.154 −0.361 Patient name −0.212 0.448 0.185 −0.113 Factor 3: Comprehensive checking Specifications −0.138 0.174 0.755 0.352 Prescription number −0.012 −0.2 0.734 0.088 Patient height and weight 0.031 0.045 0.683 −0.288 Factor 4: Detection of dosage errors Dosage −0.165 −0.038 0.092 0.827 Drug Name 0.384 0.017 0.056 0.746 Total amount 0.093 −0.058 0.325 0.411 Variance explained 4.469 2.157 1.397 1.057 Cumulative proportion of variance explained (%)
Factor 3 consisted of the AOIs required for prescription validity and prescription-to-medication matching, such as drug specifications, prescrip- tion number, and patient height and weight. In other words, this information was used to comprehensively check whether the physician is prescribing correctly and whether the pharmacist has prepared the drug as prescribed. Therefore, this was called comprehensive checking.
Factor 4 consisted of AOIs used to check the validity of the drug dosage. This was called detection of dosage errors.
Table 3 lists the factor scores for each check. The relationships between checks by participant 2 and factor 1, participant 3 and factor 2, and par- ticipant 1 and factor 3 were strong. Participant 1 focused on AOIs for comprehensive checking, participant 2 focused on AOIs for administration, and participant 3 focused on AOIs for a patient’s disease. For factor 4 (AOIs on dosage), all the participants gazed.
Table 3. Factor scores for each check (sub A-B: A is the participant number in Table 1, and B is the check number).
Table available in the original PDF paper.
Factor 1 Factor 2 Factor 3 Factor 4 Sub 2–4 4.330 −0.933 −0.729 1.594 Sub 2–2 0.552 −0.982 −0.771 0.165 Sub 4–1 −0.094 −0.935 −1.104 −0.132 Sub 3–4 −0.658 2.136 −0.421 −0.106
Sub 3–3 −0.723 1.934 −0.585 −0.314 Sub 3–6 −0.404 1.449 0.761 −0.266 Sub 3–7 −0.353 1.303 0.148 −1.403 Sub 3–5 −0.262 1.223 −0.347 0.871 Sub 3–8 −0.411 1.156 0.008 −0.273 Sub 3–2 −0.486 0.618 −0.008 −2.389 Sub 1–6 0.432 0.002 2.210 1.656 Sub 1–5 0.099 −0.352 1.969 −0.848 Sub 1–2 0.262 −0.106 1.095 −0.827 Sub 1–4 0.164 −0.567 1.056 −0.771 Sub 1–3 −0.728 −0.087 0.837 −1.550 Sub 1–1 −0.319 −0.055 0.351 −1.154 Sub 4–2 0.090 −0.789 −0.220 2.069 Sub 1–7 0.333 −0.242 0.458 1.709 Sub 2–3 −0.078 −0.983 −0.791 0.923 Sub 3–1 −0.414 −0.759 −0.213 0.786 Sub 4–3 −0.153 −0.864 −0.823 0.575 Sub 2–1 −0.346 −0.569 −0.472 0.080 Sub 4–4 −0.298 −0.830 −1.169 0.014
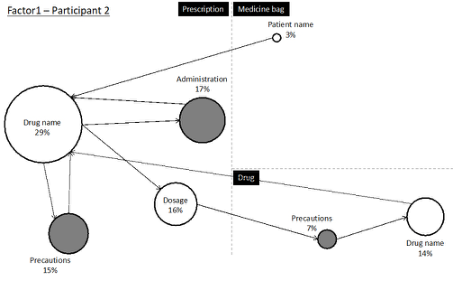
Figure 3: Typical scan path for factor 1 (detection of administration errors).
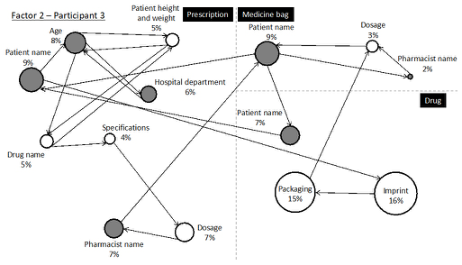
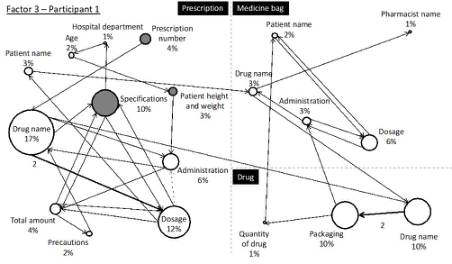
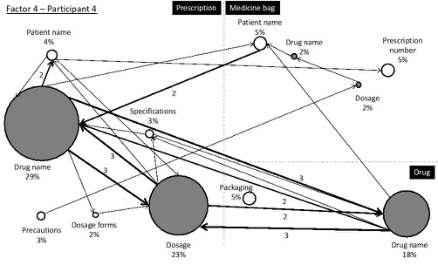
Figures 3–6 show the scan paths for the checks that are representative of each factor. The grey circles indicate AOIs that are strongly related to each factor. First, the scan path of factor 1 (see Figure 3) was simple, with a small number of AOIs and eye movements between the AOIs. Administra- tion and precautions were intensively gazed. Next, the scan path of factor 2 (see Figure 4) showed many eye movements between age, patient name, department, and drug name on the prescription. In other words, after a thor- ough understanding of the patient’s disease based on the prescription, the consistency between the patient’s disease and drug was checked. The scan path of factor 3 (see Figure 5) were the most AOIs in the prescription, and they were exhaustively gazed at. The validity of the physician’s prescription was checked based on the patient’s disease information, and the pharmacists’
Clarification of Drug-Checking Strategies for Expert Pharmacists Based on Gaze Analysis 115
drug preparation errors were checked based on the drug specifications and prescription number. The scan path of factor 4 (Figure 6) had a long gaze duration for the drug name and dosage, concentrating on the information necessary to validate the drug dosage. There was also frequent eye movement between the name of the drug on the prescription and name of the drug on the medication, as well as cross-checking of prescriptions and medications.
Figure 4: Typical scan path for factor 2 (detection of inappropriate prescription for symptoms).Figure 5: Typical scan path for factor 3 (comprehensive checking).Figure 6: Typical scan path for factor 4 (detection of dosage errors).
116 Maeda
DISCUSSION
In this study, we identified a drug-checking strategy based on the gaze pat- terns of expert pharmacists. Consequently, the following four check strategies were identified: The first check strategy focused on the detection of administrative errors. Participant 2 was strongly associated with this strategy. Participant 2 tended to have a lower number of AOIs, lower mean number of eye movements, and longer mean duration of fixation than the other participants. As the scan path is very simple, it focuses on detecting administration errors, thereby making the check more efficient. Administration errors account for 34% of preventable drug events (Bates et al. 1995; Raban and Westbrook, 2013). If a physician’s instructions for administering medication are incorrect, the nurse or patient who implements them may make errors that could cause serious harm to the patient. These facts are considered important by experts, and as a result, AOIs related to the prevention of administration errors are considered important.
The second strategy emphasized the detection of prescriptions that are inappropriate for the patient’s disease. Participant 4 was strongly associated with this strategy. Participant 4 focused on information from the prescrip- tion to understand the patient’s disease (patient age, hospital department, etc.). Although contraindications between drugs can be easily detected by electronic medical record systems, it is difficult to automatically check the contraindications of drugs for a patient’s disease (Kunitsu et al. 2020), and human checks by pharmacists are important. It is likely that the experts were aware of this and focused their checks on patient information regarding prescriptions.
The third strategy was to comprehensively check for prescriptions. Par- ticipant 1 was strongly associated with this strategy. Participant 1 had the highest number of AOI references for prescription. The validity of the pre- scription by the physician and drug preparation errors by the pharmacist were checked in a balanced manner. Generally, there are three types of safety checks (Matsui et al. 2008). A surface check reconciles the prescription with the matching drug. A logic check detects contraindications between drugs and checks the logic based on these rules. A context check is used to detect the drug’s validity for the patient’s disease and check its validity for the tar- get situation. For proofreading, context check is more accurate than surface check (Nihei et al. 2002). Pharmacists must balance surface and logic/context checks (drug validity checks) (Japan Medical Safety Research Organization, 2022). The check strategy of participant 1 appeared to balance these forms of checks.
The fourth strategy focused on drug dosage. This strategy was imple- mented for all the participants. As with the first check strategy, the high tendency of physician prescription errors regarding dosage was considered important by all the experts.
Implementing these four check strategies in a balanced manner is essen- tial. However, various experts employed different verification strategies. This indicates that the accuracy of error detection depends on the pharmacist
Clarification of Drug-Checking Strategies for Expert Pharmacists Based on Gaze Analysis 117
responsible for the check. Novice pharmacists are often trained by mentors through on-the-job training (Kasashi et al. 2015). In other words, novices may inherit only the check strategies of their assigned mentors and may not learn all four check strategies in a balanced manner. In the future, it will be necessary to develop educational methods to comprehensively transfer these check strategies to novices.
This study has several limitations. The experimental environment was not controlled because the gaze measurements were conducted in a clinical setting. Specifically, the amount and content of drugs differed among the patients, which may have affected the check strategy. Additionally, because only experts were included in the study, it was not possible to verify whether the results were expert-specific. In the future, novices should be added to the participant population and their check strategies should be compared. Since the number of the participants were four, the check strategies should be con- sidered individualized, and the number of participants should be increased in future studies.
CONCLUSION
In this study, pharmacists’ gaze was analyzed to identify check strategies based on expert gaze patterns. Consequently, four check strategies were iden- tified. In the future, it will be necessary to verify the validity of these strategies in terms of safety and develop a method for comprehensively educating novices on these strategies.
ACKNOWLEDGMENT
I would like to thank Editage (www.editage.com) for English language editing.
FUNDING SOURCES This study was supported by the JSPS KAKENHI (Grant Number JP23K04309).
REFERENCES
Aoki, H., Seki, S., Nishimagi, H., et al. (2019). Visual Perception Patterns in Clinical Reasoning Processes During Diagnosis of Infant Epilepsies: Comparisons of Eye Movement among Nurses and Students Considering their Expertise Levels. The Japanese journal of ergonomics, Volume 55 Issue 5, pp. 200–211. Aoki, H., Suzuki, S. (2010). Gaze metrics for efficient and safe operations of
hemodialysis. Proceedings of the 7th International Conference on Methods and Techniques in Behavioral Research, Eindhoven. Arakawa, N. (2022). Eikoku no Yakuzaishi no Yakuwari to Yakugaku Kyoiku no Henkaku (The Role of Pharmacists and the Transformation of Pharmacy Edu- cation in the United Kingdom), Japanese Journal of Community Medicine and Pharmaceutical Sciences, Volume 9, No. 1, pp. 59–61 [in Japanese].
118 Maeda
Bates D, Cullen D, Laird N, et al. (1995). Incidence of adverse drug events and potential adverse drug events: Implications for prevention. JAMA, Volume 274, pp. 29–34. Council of Europe. (2007). Creation of a better medication safety culture in Europe:
Building up safe medication practices. Expert group on safe medication practices (P-SP-PH/SAFE). Available: https://optimiz-sih-circ-med.fr/Documents/Council_ of_Europe_Medication_Safety_Report_19-03-2007.pdf [Accessed 16 Jan 2024]. Fukuda, R., Sakuma, M., Nakamura, E., et al. (1996). An experimental consideration on the definition of a fixation point. The Japanese journal of ergonomics, Volume 32 Issue 4, pp. 197–204. Hirano, Y., Kodawara, T., Igarashi, T., et al. (2017). Preventive Effect for Dispens-
ing Errors and Incidents by Drug Verification and Quantity Management System Using Personal Digital Assistants and Medicine Barcodes, Japanese Journal of Pharmaceutical Health Care and Sciences, Volume 43 Issue 9, pp. 502–508. Itoh, K., Hansen, J. P., Nielsen, F. (1998). Cognitive modelling of a ship navigator based on protocol and eye-movement analysis. Le Travail Humain, pp. 99–127. Japan Medical Safety Research Organization. (2022). Recommendations for the
prevention of recurrence of medical accidents (Number 15) Analysis of Deaths Related to “Erroneous Administration of Medicine”. Available: https://www.me dsafe.or.jp/uploads/uploads/files/teigen15english.pdf [Accessed 16 Jan 2024]. Kasashi, K., Miyamoto, T., Harada, S., et al. (2015). Development and Evaluation of an Educational Program for Newly Graduated Pharmacists, Japanese Journal of Pharmaceutical Health Care and Sciences, Volume 41 Issue 8, pp. 533–539. Kawamoto, T., Tominaga, M., Ohshita, M., et al. (2009). Influence of a combined
authentication system and computerized physician order entry system on quality and quantity in near-miss medication reports, The Journal of Japan Society for Health Care Management, Volume 10 Issue 2, pp. 443–448. Kunitsu, Y., Hira, D., Uenishi, K., et al. (2020). Evaluation of Usefulness of Check System for Contraindications for Diseases Linked with Electronic Medical Record System, Japanese Journal of Pharmaceutical Health Care and Sciences, Volume 46 Issue 9, pp. 489–502. Matsui Y, Goto M, Shimadate Y, et al. (2009). The Relationships between Checking
Methods and Error Types on Error Detection for Writings, Numeric Tables, and Drawings, INSS journal: Journal of the Institute of Nuclear Safety System, Volume 16, pp. 2–13. Morita, J., Fujimoto, N., Yanagita, K. (2018). Approach to the transfer of quality control skills at the construction site using eye-gazing data, Proceedings of the Annual Conference of JSAI, Volume. JSAI2018, 32nd, p. 1M202. Nihei, Y., Terashima, M., Suzuki, I., et al. (2002). Why are four eyes better than
two? Effects of collaboration on the detection of errors in proofreading. Japanese Psychological Research, Volume. 44, pp. 173–179. Raban, M. Z., Westbrook, J. I. (2013). Are interventions to reduce interruptions and errors during medication administration effective?: A systematic review. BMJ quality and safety. Shah, K., Lo, C., Babich, M., et al. (2016). Bar code medication administration
technology: A systematic review of impact on patient safety when used with com- puterized prescriber order entry and automated dispensing devices. Can J Hosp Pharm, Volume 69, pp. 394–402. Sheikh, A., Rudan, I., Cresswell, K., et al. (2019) Agreeing on global research priorities for medication safety: An international prioritization exercise. J Glob Health, Volume 9, p. 010422.
Clarification of Drug-Checking Strategies for Expert Pharmacists Based on Gaze Analysis 119
Udagawa, Y. (2020). Study on Technique Transmission and Skill Transmission in the Building Facilities Part 1 Verification of Construction Quality Inspection by Eye-tracking, Technical Papers of Annual Meeting the Society of Heating, Air- conditioning and Sanitary Engineers of Japan, Volume 1, pp. 129–132. Vosper, H., Hignett, S. (2018). A UK Perspective on Human Factors and Patient
Safety Education in Pharmacy Curricula, American Journal of Pharmaceutical Education, Volume 82 Issue 3, p. 6184. Wahr, J. A., Shore, A. D., Harris, L. H., et al. (2014). Comparison of Intensive Care Unit Medication Errors Reported to the United States’ MedMarx and the United Kingdom’s National Reporting and Learning System. Am J Med Qual, Volume 29, pp. 61–69. World Health Organization. (2017) Medication Without Harm -Global Patient
Safety Challenge on Medication Safety. Geneva: World Health Organization. Yamashina, H., Kano, S., Suzuki, T., et al. (2019). Assessing Visual Attention of Mammography Positioning Using Eye Tracking System: A Comparison between Experts and Novices, Japanese Journal of Radiological Technology, Volume 75, Issue 11, pp. 1316–1324.
LISTED IN THE AHFE DIGITAL BOOKSTORE CATALOGUE
Explore the complete digital volume
Healthcare and Medical Devices
Read this individual research paper free through the original publisher, or explore the full digital proceedings book.
ISBN 978-1-964867-06-9
Explore this ISBN in the AHFE Bookstore ↗Listed in the July 2026 bookstore catalogue; search by ISBN to confirm current availability · Digital book purchase optional